

Don’t Keep Financing a Secret: How to Promote Patient Financing in Your Practice Marketing

Your practice offers patient financing. Your front desk knows about it. Your treatment coordinators mention it during consultations. But do patients know about it before they walk through your door?
For many practices, the answer is no. Financing often stays hidden until the very end of the patient journey, after the patient has already worried about cost, delayed booking, or chosen a competitor who talked about affordability sooner. Promoting patient financing early in your marketing can help patients see treatment as achievable from the start. With Alphaeon Credit, practices can offer patients financing options with promotional plans such as no interest if paid in full, and put those options to work across the entire patient journey.
Here’s how to bring financing out of the back office and into your marketing strategy.
Why Cost Concerns Start Before the Consultation
Patients often research treatment long before they call your office. They compare practices, read reviews, and search for prices. When cost seems out of reach, many never schedule a consultation at all.
Promoting financing early can help:
Reduce Hesitation: Patients who know financing is available may feel more comfortable booking.
Attract Qualified Leads: Patients arrive already aware that payment options exist.
Shorten the Decision Process: Financing conversations happen sooner and more naturally.
Differentiate Your Practice: Highlighting flexible payment options can help you stand out from competitors.
Support Larger Treatment Plans: Patients may feel more open to comprehensive care.
Where to Promote Financing
Patients interact with your practice across many touchpoints. Consider adding financing messaging to each of them.
Your Website
Your website is often the first impression of your practice. Consider:
A Dedicated Financing Page: Explain your payment options clearly and simply.
Service Page Mentions: Add a short note about financing on pages for elective or higher-cost treatments.
Homepage Visibility: Include a financing link or banner so patients don’t have to search for it.
Pre-Qualification Links: Make it easy for patients to check their options before they call, when available.
Social Media
Social media is a great place to normalize conversations about affordability:
Educational Posts: Explain how financing works in simple terms.
Treatment Spotlights: Pair before-and-after content with a reminder that payment options are available.
Stories and Reels: Share quick tips about planning for treatment.
Email and Text Campaigns
Reach existing patients who may be ready for treatment:
Reactivation Campaigns: Remind patients who delayed treatment that financing is available.
Seasonal Promotions: Tie financing messages to timely moments, like the end of the year or the holiday season.
Treatment Reminders: Include financing information in follow-ups after consultations.
In the Office
Don’t forget about patients who are already in your practice:
Waiting Room Signage: Display financing information where patients can see it.
Printed Materials: Include financing details in treatment plan folders.
Digital Screens: Add financing messaging to in-office displays.
Keep Your Messaging Clear and Compliant
When promoting financing, clarity and compliance matter. Credit advertising is regulated, and certain terms, such as specific payment amounts, interest rates, or promotional periods, may require additional disclosures.
To help keep your practice on the right track:
Use Approved Materials: Take advantage of marketing materials and resources provided through your financing partner.
Avoid Overpromising: Don’t guarantee approval or specific terms. Approval depends on each patient’s credit review.
Include Required Disclosures: Follow your financing partner’s guidelines on promotional terms and fine print.
Keep Messaging Simple: Focus on flexibility and affordability without making misleading claims.
Check With Your Compliance Resources: When in doubt, confirm messaging before publishing.
This blog is for general informational purposes and isn’t legal or financial advice. Always follow applicable regulations and your financing partner’s guidelines.
Use Patient Stories to Build Trust
Patients often feel more comfortable when they see others like them moving forward with treatment. With patient permission and in line with privacy rules, consider sharing stories that show how flexible payment options helped patients get the care they wanted. Keep the focus on the patient’s experience and results, and avoid implying that every patient will qualify for the same terms.
Train Your Team to Reinforce the Message
Marketing brings patients in, but your team helps turn interest into scheduled treatment. Make sure your staff can:
• Explain Financing Simply: Patients appreciate straightforward answers.
• Bring It Up Early: Mention payment options before patients raise cost concerns.
• Guide the Application Process: Help patients understand how to apply and what to expect.
• Follow Up: Reach out to patients who expressed interest but didn’t schedule.
Alphaeon Credit provides practices with onboarding, training, and marketing support to help teams present financing with confidence.
Why Timing Matters in Q4
The final months of the year are a natural time to promote financing. Many patients are thinking about year-end benefits, holiday events, and New Year goals. Marketing financing now can help patients plan treatment they may have been putting off and help your practice finish the year strong.
Patient Financing Marketing FAQs
Should I mention financing on every page of my website?
Focus on pages for higher-cost or elective treatments, along with a dedicated financing page.
Will promoting financing make my practice seem less premium?
When presented thoughtfully, financing can position your practice as patient-focused and accessible.
Can I advertise specific payment amounts?
Advertising specific credit terms may require additional disclosures. Use approved materials and follow compliance guidelines.
How do I measure success?
Track financing applications, consultation bookings, and case acceptance before and after launching your marketing efforts.
Put Patient Financing to Work With Alphaeon Credit
Patients can’t choose financing if they don’t know it’s available. By promoting payment options throughout your marketing, you can help more patients move forward with the care they want.
Learn how Alphaeon Credit can support your practice with flexible patient financing, easy enrollment, and dedicated marketing resources. Visit the practice support section of the Alphaeon Credit website to get started.

Preparing Pet Parents for the Cost of Care
A pre-visit communication framework for veterinary practices, from Alphaeon with insights from Debbie Boone, CVPM, and Gigi Santos, LCSW, of Not One More Vet.
Executive summary
Veterinary practices can protect patient outcomes, client trust and team well-being by preparing pet parents for the cost of care before they arrive, not at checkout.
Rising fees, falling visit numbers and stretched household budgets make this urgent. This paper explains why cost conversations get avoided, what that costs clients and teams, and offers a three-stage framework and checklist practices can adopt now.
1. The problem: an expectation gap meets a strained budget
Pet parents underestimate the cost of care, and their budgets have little room to absorb the surprise.
Clients don't know what care costs
Research by Dr. Karen Felsted found owners estimated exam and vaccine costs fairly accurately, but expected a dental cleaning to cost about $55. A grade 1 dental today can exceed $650. Most clients also know little about anatomy or disease, so explanations that assume basic knowledge can leave them confused and defensive.
Online information doesn't close the gap. An AI query for a routine visit in Greensboro, North Carolina returned exam fees, vaccine ranges and clinic prices where a single vaccine varied by more than double. A client facing that spread is more likely to delay than to decide.
Households are stretched
| Indicator | Figure cited in the webinar |
|---|---|
| U.S. household debt | About $18.8 trillion |
| Americans living paycheck to paycheck | One-third to two-thirds, depending on the survey |
| Would need to borrow for a $1,000 emergency | 43% |
| Typical routine visit invoice | Over $200 |
| Lifetime cost of ownership (all-inclusive) | Up to $60,000 for a dog; over $47,000 for a cat |
Practices are feeling it
Economist Dr. Matt Salois describes a "veterinary recession": visits decline while revenue rises slightly on higher fees. Practices report open appointments that were unheard of two years ago. Loyal clients are moving to vaccine clinics, shelters and feed stores, or waiting to see if a symptom passes.
The downstream pattern is consistent across downturns: preventive care is deferred, urgent cases rise, and relinquishment and economic euthanasia increase.
2. Root causes: why cost conversations get delayed
Practices routinely discuss diet, training, dental care and harnesses. Cost is the topic most often left until circumstances force it.
| Barrier | How it shows up |
|---|---|
| Cultural discomfort | Talking about money feels rude or greedy; teams fear sounding like a pushy salesperson. |
| No formal training | Few team members have been taught how to discuss finances or explain the value behind a fee. |
| The timing trap | Too early feels insensitive; too late leaves the client blindsided and distrustful. |
| Fear of rejection | A declined estimate feels like failing the doctor and the patient. |
| Under-informed front desk | CSRs field cost questions without the medical context to answer them, so questions get bounced between staff. |
| Restrictive policies | Some practices refuse to quote even routine prices by phone, which reads to clients as hiding something. |
| Rushed appointments | Education takes time; a five-minute visit leaves none for it. |
Boone's reframe is the starting point for change: "Talking about money is part of patient care, and you cannot separate the two."
3. The human impact on clients and teams
Uncertainty about cost raises emotional intensity on both sides of the exam table, and that intensity degrades care and communication.
For pet parents
Even routine visits carry low-level fear: the doctor might find something unexpected, or the pet's weight or age might prompt guilt. Unknown costs compound it. In emergencies, Boone describes clients in a "limbic hijack" so intense that the team cannot take an accurate history. Clients who aren't told about fees often don't object in the moment. They pay, then tell friends how expensive the visit was, eroding the word-of-mouth that builds "raving fans."
For veterinary teams
Santos frames client education as a workforce well-being strategy. When teams lack answers or resources for financial conversations, NOMV sees:
anxiety before and during cost discussions;
discomfort and avoidance around particular clients;
moral distress when care must be declined or euthanasia is chosen for financial reasons;
cumulative stress that contributes to burnout and turnover.
The reverse is also true. Santos, an owner of five pets including a Boston Terrier with a seizure disorder, describes how preparing for visits lowered her own emotional intensity, and her care team's. Prepared clients communicate more clearly, slow down, and make decisions with less conflict. That protects team workflow and makes healthy boundaries easier to hold.
4. The framework: three stages of cost communication
Cost communication works best as a continuous practice that begins before the client arrives, not a single conversation at checkout.
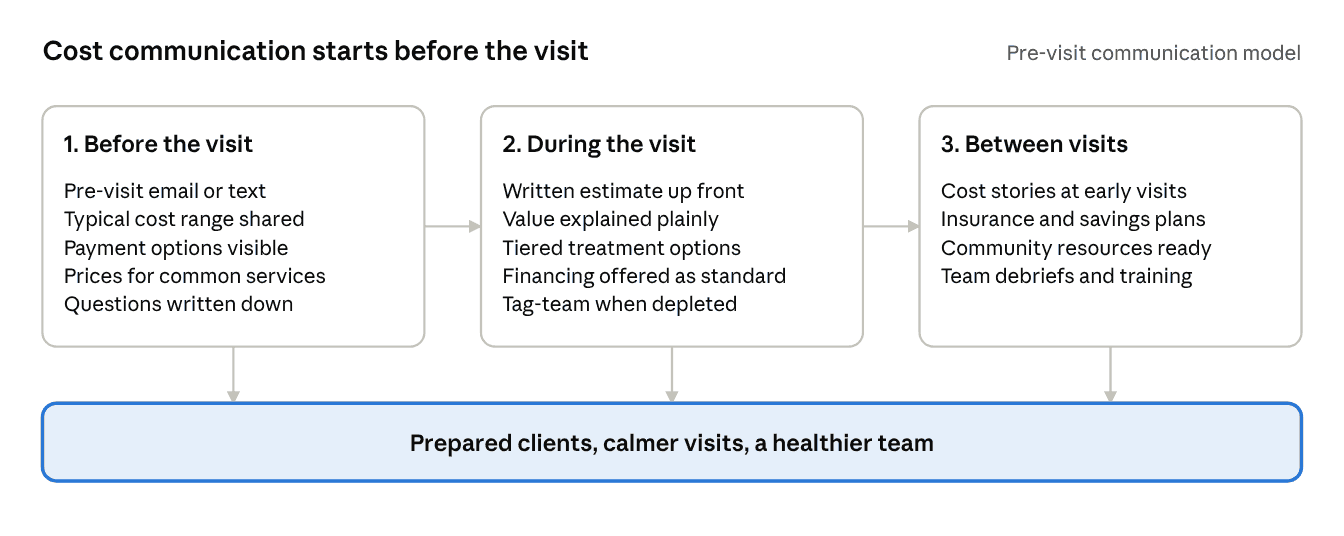
Each stage lowers uncertainty for the next. A client who received a cost range before the visit hears the estimate as confirmation, not shock. A client who heard cost stories at a puppy visit is more likely to have insurance, savings or a financing plan when an emergency comes.
5. Implementation checklist
Practices can adopt most of these steps within a quarter, without new technology.
Before the visit
☐ Add a pre-visit email or text template: records and medication list, written questions, arrive early, bring leash or carrier, flag an anxious pet.
☐ Include the typical cost range for the scheduled service in that message.
☐ List every accepted payment and financing option on the website, social profiles, reminders and handouts.
☐ Decide whether to publish prices for common services, each with what is included and why.
☐ Allow trained team members to quote routine prices by phone.
During the visit
☐ Present written estimates before treatment, without the client having to ask.
☐ Explain value in plain language; avoid assuming medical knowledge.
☐ Offer tiered treatment options when gold-standard care is out of reach.
☐ Present financing as a standard option, not a last resort.
☐ Use a tag-team or handoff when a team member is depleted.
Across the relationship
☐ Share real cost stories at puppy and kitten visits to encourage insurance and savings.
☐ Train front-desk staff on common diagnoses and the value of core services.
☐ Keep a current list of community partners and charitable funds.
☐ Debrief after difficult cases, and celebrate wins.
☐ Schedule appointments long enough for education.
Payment-option toolkit
No single tool fits every client. Practices should be ready to discuss each.
| Option | Best for | Note |
|---|---|---|
| Patient financing (e.g., Alphaeon) | Planned procedures and unexpected costs | Promotional terms such as 24 months no interest if paid in full, with longer terms up to 60 months, subject to credit approval |
| Pet insurance | Large, unpredictable costs over the pet's life | Most valuable when enrolled young |
| Wellness or savings plans | Routine and preventive care | Spreads predictable costs across the year |
| Traditional credit cards | Smaller balances | Interest may apply |
| Charitable funds (e.g., Veterinary Care Foundation) | Clients who don't qualify for other options | Some practices also arrange donor-client support funds |
| Alternative treatment plans | When gold-standard care is unaffordable | Still provides relief for the patient |
6. Measuring success
Track a small set of indicators before and after adopting the framework:
Client: estimate acceptance rate, routine visit volume and preventive-care compliance, online reviews mentioning cost or communication.
Financial: financing application volume, share of invoices paid in full at checkout, accounts receivable.
Team: staff turnover, self-reported stress around financial conversations, and baseline-to-follow-up results from a well-being assessment such as NOMV's Clear Blueprint certification.
7. Conclusion
Client trust is a practice's most valuable asset, and it is built by being forthcoming about the reality of pet care, including its cost. The practices that thrive through this downturn will treat the cost conversation not as an awkward afterthought, but as part of the standard of care.
About the contributors
Debbie Boone, CVPM, owner of Debbie Boone Consulting, has worked in veterinary hospitals since 1985 and helps practices improve operations and client experience.
Gigi Santos, LCSW, is CEO of Not One More Vet, a global nonprofit founded in 2014 to support mental health and well-being in the veterinary profession. Free resources are available at nomv.org.
Rafael Velasco of Alphaeon moderated the webinar.
About Alphaeon: Alphaeon provides patient financing that helps veterinary practices offer flexible payment options, so more pet parents can say yes to the care their pets need.
Sources
Figures in this paper are as cited by the speakers during the Alphaeon webinar "Pause and Peace of Mind: Helping Pet Parents Prepare for Cost Before the Visit." They include research by Dr. Karen Felsted on owner cost perceptions, commentary by economist Dr. Matt Salois, and national consumer-finance surveys. Verify and link primary sources before external publication.

Patient Financing as Access Infrastructure in a Constrained Audiology Market
Why every patient encounter now carries more economic weight — and what it unlocks for the patient is what makes financing infrastructure rather than a sales tool
Amyn M. Amlani, PhD
Audiologist | Health Economist | Professor and Chair, Department of Communication Sciences and Disorders, University of Oklahoma Health Sciences Center
Executive Summary
Declining third-party reimbursement and constrained provider capacity have changed the economics of every patient encounter in audiology. Whether a patient who needs treatment proceeds with it is now a determinant of practice viability, not a sales statistic. And what that encounter delivers, when it succeeds, is consequential: measurable improvement in the patient’s communication, participation, and quality of life. Patient financing, understood correctly, is access infrastructure — the mechanism that connects a patient who needs care to care that changes their life.
For two decades, patient financing in hearing care has been framed as a sales tool: a way to close more units, lift average selling price, or overcome a price objection. That framing is now obsolete, and it was always too small. The economic ground under audiology has shifted structurally, and the shift changes what financing is for.
Three forces are converging. First, third-party administrators (TPAs) and Medicare Advantage (MA) benefit structures are compressing the revenue a practice realizes per fitting.¹ Second, the audiology workforce is not growing fast enough to meet demographic demand,² which makes clinician time — not patient volume — the limiting factor on a practice. And third, over-the-counter (OTC) hearing aids have established a public reference price that suppresses willingness to pay for professional care upstream of the encounter itself.³ Together, these forces mean that every patient who reaches the point of decision now carries more economic weight than at any point in the field’s history.
That economic weight is only one-half the argument. The other half is what the encounter is worth to the patient. Untreated hearing loss is associated with measurable decline in communication, social participation, and emotional well-being. A patient who agrees they need treatment and then walks away at the financial decision is not a lost sale. They are a person left with an avoidable barrier to care — and with the communication, participation, and quality-of-life consequences that follow.
Financing, designed and positioned as access infrastructure rather than as a sales instrument, addresses exactly this failure point. It does not solve the workforce shortage and it does not reverse reimbursement compression. What it does is convert demand the practice has already earned into care the patient actually receives — the single most actionable lever most practices and networks have. This paper sets out the economics, what is at stake for the patient, why conversion has become an operational rather than a commercial question, the access reframe at the center of the argument, what financing does and does not do, what it implies for operators and for financing partners, and where the market is heading.
1. The Changing Economics of the Encounter
The economics of a hearing care encounter were, for a long time, stable. A patient presented, was evaluated, was fit, and the practice realized a margin sufficient to support the clinical time invested. That stability has eroded from three directions at once, and the erosion is structural, not cyclical.
What the patient is actually paying for
The cost a patient confronts has three parts: (1) diagnostic services, (2) the device itself, and (3) professional services — the counseling, fitting, verification, and follow-up care that determine whether the device is used and the outcome is achieved. Some practices bundle these into one price; others itemize. Either way, the patient is paying for clinical expertise and ongoing care, not for a retail object. The payment conversation routinely obscures that distinction, and financing, positioned correctly, helps restore it.
Reimbursement compression
A growing share of patients now arrive through TPAs and managed-benefit channels rather than as private-pay patients. In these arrangements the administrator sets the device options, the patient’s share, and the fee the provider receives — a controlled and substantially lower margin than historical private-pay pricing. The consequential mechanism is not the existence of TPAs but the shift in patient mix: as MA enrollment grows as a share of the Medicare-eligible population, more patients arrive through a benefit carved out to a TPA rather than paid at the practice’s standard rate.¹ Even with flat volume, average revenue per encounter falls because the mix is tilting toward structurally lower-margin channels, as shown in the figure below.
The gap between perceived and actual coverage
A distinct pressure operates at the moment of decision: the gap between what patients believe their plan covers and what it actually covers. Many MA enrollees choose plans expecting meaningful hearing benefits, but most MA hearing benefits function as capped allowance or discount programs — a fixed dollar amount, specific device tiers, narrow networks, professional services thinly covered or excluded. Patients often learn the true scope of their responsibility only at the point of recommendation. That is not an administrative inconvenience; it is an affordability shock delivered precisely where the decision is made, and it is financing-addressable in a way the underlying reimbursement structure is not.
Price anchoring from the over-the-counter market
The regulated OTC category introduced a third pressure, and its most consequential effect is not the one most often cited. The direct displacement of lowest-complexity fittings is real but bounded — OTC reaches a segment of consumers who were unlikely to seek professional care at prevailing prices regardless. The more durable effect operates upstream of the encounter entirely: OTC has established a visible public reference price for a hearing aid, and that price point shapes what prospective patients believe they should have to pay before they make an appointment, read a brochure, or speak with a clinician. The anchor is not formed in the consultation room; it arrives with the patient. Research on price anchoring in consumer health decisions confirms that externally formed reference prices suppress willingness to pay for higher-cost alternatives even when the quality differential is understood and accepted — the gap between what patients expect to pay and what professional care costs has widened, not because clinical value has diminished, but because the retail baseline has moved.³
There is a second effect the displacement story misses. If OTC selectively captures the least complex presentations — patients with mild to moderate, uncomplicated loss who are comfortable with self-fitting — then the patients who continue to seek professional care are, on average, more complex. More complex cases require more clinician time per encounter. This means OTC exerts quiet upward pressure on the time cost of each professionally managed case, compounding the capacity constraint described in the next section, and reinforcing why the value realized from each hour of clinical time has become the metric that governs practice viability.
The cumulative effect
Reimbursement compression, the coverage-perception gap, and price anchoring reach the same result by different routes: the economic contribution of the average encounter has fallen. That is the foundation for everything that follows. But the economic argument only acquires its force once it is clear what the encounter is worth when it succeeds.
2. What Is at Stake for the Patient
Every argument in this paper rests on a premise the sales framing leaves unstated: the encounter, when it ends in appropriate treatment, produces consequential improvement in the patient’s life, and when it fails, the patient bears a real and avoidable cost. Financing is infrastructure rather than tactic precisely because of what sits on the other side of it.
Hearing loss is among the most prevalent and most undertreated chronic conditions, and its consequences are not confined to audibility. Untreated hearing loss is associated with reduced communication function,⁴ withdrawal from social participation and strained relationships,⁵ diminished workforce engagement and earnings,⁶ and elevated risk of depression and isolation.⁷ Treatment does not merely restore detection of sound; it restores the patient’s capacity to participate — in conversation, in relationships, in work, in community. These are the outcomes that determine quality of life, and they are precisely the outcomes a financed treatment plan makes reachable for a patient who would otherwise have declined.
The encounter also carries value beyond hearing itself: it is an accessible point of contact at which broader health concerns can be identified and routed, through appropriate referral, into the rest of the care system. The fuller development of that point belongs to the peer-reviewed literature and is not pursued here. The operative consequence for this paper is narrower and sufficient: when a patient who needs care is lost at the financial decision, what is forfeited is not only a device and not only the practice’s realized value for that hour, but the patient’s connection to a care relationship whose value is, on the evidence, larger than the transaction. The cost of the lost encounter is a health cost, not merely a revenue one.
3. Why Conversion Became an Operational Question
Falling margin per encounter cannot simply be offset by seeing more patients, because the limiting factor in audiology is not demand. It is clinician supply. Demographic aging is expanding the population with clinically significant hearing loss faster than the profession produces audiologists to serve it, and clinician hours cannot be scaled quickly: the training pipeline is long and the attrition and distribution dynamics are unfavorable (figure adapted from data provided in Bray & Amlani²).
When clinician time is the scarce resource, the metric that governs the business is not units sold or patients seen. It is the value a practice realizes from each hour of that time. Sophisticated operators increasingly use exactly this measure when deciding whether to hire, expand, or add a service line — evidence that the field’s own commercial logic has already moved here, even where the vocabulary lags.
That reframing changes how every downstream decision should be evaluated, financing included. If a practice cannot add hours, it can only improve performance by raising the value of each hour or reducing the share of hours that yield nothing.
The point can be stated simply. If a clinic has 100 recommendation encounters per month and 20 patients decline because of immediate affordability, even modest recovery of those patients changes the yield of the same clinician hours. Financing improves the access yield of capacity already being consumed.
An encounter that ends with the patient agreeing to treatment but unable to pay for it is a fully consumed hour of the scarcest resource the practice has — with no revenue and, the point of the prior section, no treated patient. In a capacity-constrained system that is the most expensive outcome there is, on both ledgers.
This is why conversion has migrated from a sales concept to an operational one. In a capacity-rich business a lost close is a missed opportunity the next patient replaces. In a capacity-constrained business with falling margin, a lost close is an irrecoverable loss of the scarcest resource the practice has — and a person left untreated.
4. Affordability Is an Access Barrier, Not a Sales Objection
The conventional framing treats a patient who declines for cost as a sales failure — an objection that was not overcome. That framing is not only commercially limiting; it is wrong, and the error determines how the problem gets addressed.
A patient who has been evaluated, received a recommendation, and agrees with it has already done the hard work of accepting that they have a problem and that treatment is warranted. The literature on consumer decision-making in hearing care — including the path from problem recognition to action — locates the decisive barrier not at clinical persuasion but at financial activation.⁸ The patient is not unconvinced. They are, at that moment, unable to absorb the cost. That is an access barrier, and the distinction from a sales objection is not semantic.
Treating it as a sales objection points toward sales responses — discounting, pressure, repackaging — each of which erodes margin, trust, or both, and none of which addresses the actual constraint. Treating it as an access barrier points toward access responses: mechanisms that let a patient who needs care proceed despite a liquidity constraint at a single moment. Financing is the most direct of these.
The sales framing also erases a real ethical cost — and it falls on both sides of the relationship. The patient who cannot afford the clinically appropriate option does not simply choose differently; they accept a known, preventable deficit, often without fully understanding that is what they are doing. The provider who watches this happen is caught between clinical obligation and financial reality: discounting to close the gap compromises the practice; withholding the full recommendation to avoid the awkwardness compromises the patient. A mechanism that lets the patient proceed on the clinically appropriate plan resolves the tension without compromising either, and preserves the trust at the center of the relationship. This is why the reframe makes financing a serious subject rather than a vendor talking point — and why a financing provider's commercial interest, properly understood, aligns with the clinical and public-health interest in getting more clinically indicated patients treated.
That alignment is the conceptual core of this paper. When affordability is the barrier, the patient’s interest in care and the well-being that follows, the practice’s interest in realizing value from a scarce hour without an ethical compromise, and the financing partner’s interest in enabling the transaction all point the same way. That alignment is unusually clean, and it is why financing belongs in the category of infrastructure, not tactic.
5. What Financing Does — and What It Does Not
Positioned correctly, financing operates at exactly the point identified above: the moment a patient who needs care confronts a cost they cannot immediately absorb. Well-designed financing converts a single-moment barrier into a manageable obligation over time, letting the patient proceed with care that has already been clinically justified. The effect is to raise the share of patients who needed care and actually receive it — which, in a capacity-constrained practice, is the same as raising the value realized from a scarce hour without adding one, and, on the human side, the same as more people receiving care that improves their lives.
Healthcare-specific financing is not retail credit
A distinction essential to both credibility and patient protection must be stated plainly. Healthcare-specific financing is not general-purpose consumer credit applied to healthcare. Revolving credit — credit cards, unstructured personal loans — tends to carry high or variable interest, revolving balances, and opaque total cost, and can compound financial stress rather than relieve it. Properly designed healthcare financing is built on fixed, transparent terms, defined repayment schedules, and integration into the care conversation rather than after-the-fact collection. The distinction matters because it defuses the most legitimate objection to financing — that it loads vulnerable patients with debt — and because it is the line between an access mechanism and a liability. An analysis that did not draw that line honestly would deserve the skepticism it received.
The boundaries, stated honestly
The credibility of the broader argument depends on its limits. Financing does not solve the workforce shortage; it creates no clinician hours. It does not reverse reimbursement compression; that margin structure is set elsewhere. It does not lower the underlying cost of care. Any claim otherwise is a brochure, and sophisticated operators will discount it accordingly.
What financing does is narrower and, because it is narrower, defensible: it converts demand the practice has already earned into care the patient actually receives, on capacity that already exists. With the two largest economic problems — clinician supply and reimbursement compression — largely outside any single practice’s control, this conversion is one of the few high-leverage variables an operator can actually move, and the only one whose improvement also advances patient well-being. Bounded claims are the ones that survive scrutiny.
A second-order effect: predictability as risk reduction
Financing that makes realized revenue per encounter more predictable also functions as a risk-reduction layer at the practice level. A practice that can rely on a more stable yield is better positioned to invest in adjacent service lines — tinnitus management, vestibular and balance assessment, and similar expansions — because the downside variance of the core business is dampened. In this view financing is not only an access mechanism for the patient; it is a stability mechanism for the practice that lowers the risk of strategic expansion. The next section develops what that implies for operators and for financing partners.
There is a patient-side analogue to this stability effect. Financing that enables a patient to proceed also tends to anchor the ongoing care relationship: evidence from medicine⁹ and dental¹⁰ healthcare categories consistently finds that structured payment arrangements — by reducing financial friction across the care episode, not only at its start — are associated with higher treatment completion and longer care relationships; there is no reason to expect hearing care to be an exception. That continuity is not incidental to outcomes — it is, in the evidence on treatment benefit, one of the primary determinants of realized gain.¹¹ Financing designed as infrastructure, therefore, improves not only the probability that a patient begins treatment but the probability that the treatment works.
6. Implications for Operators
Translated into operating terms, the argument has concrete implications for how practices and networks should treat financing — not as a point-of-sale add-on, but as a structural element of the economic model.
Evaluate it as yield, not units
The right question for an operator is not how many additional units financing moves but how much it raises the value realized from a fixed quantity of clinician time. Because that time is the binding constraint, an improvement in the share of patients who proceed flows straight to the metric that matters: the same clinicians and the same slots produce more treated patients and more realized value, with no expansion of the constraint — and, not incidentally, more patients whose lives improve. This is the framework operators already apply to expansion decisions; financing should be evaluated inside it.
It interacts with the pricing model
Under bundled pricing, financing addresses the visible total-price anchor directly by distributing it over time. Under unbundled pricing, it additionally protects the professional-services component — the ongoing care — from being the line a patient tries to cut under cost pressure. In both models the function is identical: preserving access to the full recommended plan. Networks operating mixed models should account for the difference in how financing is positioned.
It is a platform for expansion, not only a point-of-sale tool
Practices weighing investment in adjacent service lines are making a capital decision under uncertainty, and the principal uncertainty is the stability of the revenue base that must underwrite it. By making realized yield more predictable, financing lowers the variance of that base and the effective risk of expansion. For multi-site networks and corporate groups this reframes financing from a convenience into an enabling condition for portfolio growth — which maps directly onto how network leadership decides where to deploy capital.
The emphasis shifts by segment
For independent practices, financing is principally an access and survival mechanism in a compressing-margin environment. For multi-site groups and management or hearing service organizations, it is additionally a portfolio risk-management tool and an enabler of standardized expansion across sites. For manufacturer-affiliated and retail networks, it is a channel-economics lever that protects realized value as patient mix shifts toward managed channels. The mechanism is constant; the strategic emphasis moves with the buyer’s structure.
7. Implications for Financing Partners
The analysis also has implications for how a financing partner should be chosen and integrated — because the argument of this paper is only realized if the financing itself is built and positioned the way the argument requires. Not all financing is equivalent, and the difference is strategic, not cosmetic.
Three properties separate financing that functions as access infrastructure from financing that functions as a point-of-sale convenience. First, structural design: fixed, transparent terms integrated into the care conversation, not revolving credit bolted onto checkout — the distinction drawn earlier is the difference between a partner that strengthens the practice’s credibility and one that quietly erodes it. Second, workflow integration: financing has to be present at the moment of decision, inside the clinical conversation, rather than surfaced after the patient has already declined; infrastructure that arrives after the barrier has done its work is not infrastructure. Third, alignment of positioning: a partner whose own framing treats financing as access rather than as a sales accelerant reinforces the practice’s clinical posture instead of undercutting it with the patient.
Evaluated against those properties, the right financing partner is not a vendor of a transactional product but an extension of the practice’s access strategy. A partner positioned this way — Alphaeon among them — contributes more than a payment instrument: it contributes the predictability that lowers expansion risk, the transparency that protects patient trust, and the decision-point presence that determines whether a clinically willing patient actually receives care. For a network selecting a financing partner, the relevant question is, therefore, not which provider offers the most aggressive promotional terms, but which one is built and positioned to do the structural job this paper describes. That is the question the analysis points to, and it is the one worth taking into the selection.
8. Outlook
The pressures described here are not transitional. MA penetration is likely to keep rising, so the share of encounters arriving through carved-out, margin-compressed channels will grow. The OTC category will mature, and the price anchor it set will harden. The workforce constraint will tighten before it eases, because the demand curve is steeper than any realistic acceleration of the training pipeline. Every trend pushes the same way: the weight carried by each professionally managed encounter will increase, not decrease.
In that trajectory, whether a patient who needs care actually receives it moves from a useful lever to a determinant of which practices and networks remain viable — and of how many people with treatable hearing loss are treated at all. Financing built and positioned as access infrastructure is set to become a standard layer of practice economics rather than an optional add-on, in the way infrastructure becomes invisible precisely because it has become indispensable. Operators who integrate it deliberately, and partners who position it as access rather than sales, will be advantaged as the architecture stabilizes. Those who continue to treat it as a discount-adjacent tactic will capture a fraction of its value and misread the role it has come to play.
The conclusion is, therefore, straightforward, and it is worth ending on the human term rather than the economic one. The question for a practice or a network is no longer whether to offer financing. It is whether to treat it as infrastructure — designed into the economic model, positioned as access, measured by its effect on the value realized from scarce clinical time, and understood as the mechanism that connects a patient who needs care to an outcome that materially improves their life — or to leave that value, and that outcome, unrealized. The analysis here indicates the first posture is the one consistent with where the market is going, and the only one consistent with what the encounter is actually for.
References
Diles W. The managed care manifesto. The Hearing Journal. 2021 August; 74(8):27-28.
Bray V, Amlani AM. (in press). Audiology workforce supply and population demand: Trends, benchmarks, and implications. Seminars in Hearing.
St. Jean CR, Cummine J, Singh G, Hodgetts W. Exploring the Influence of Online Price Anchoring and Attribute Framing on the Likelihood of Hearing Aid Purchases. Audiology Research. 2025;15(2):40
Lin FR, Albert DS. Aging and hearing health: The life-course approach. Gerontologist. 2016;56(Suppl 2):S220-S233.
Weinstein BE, Ventry IM. Hearing impairment and social isolation in the elderly. Journal of Speech and Hearing Research. 1982;25(4):593–599.
Emmett SD, Francis HW. The socioeconomic impact of hearing loss in US adults. Otolaryngology–Head and Neck Surgery. 2015;152(3):545-550.
Livingston G, Huntley J, Sommerlad A, et al. Dementia prevention, intervention, and care: 2020 report of the Lancet Commission. The Lancet. 2020;396(10248):413-446.
Amlani AM. Application of the Consumer Decision-Making Model in assessing hearing aid adoption intent in first-time users. Seminars in Hearing. 2016;37(2):103-119.
McClella MB, Feinberg DT, Bach BP, et al. Payment Reform for Better Value and Medical Innovation. National Academy of Medicine Perspectives. 2017; Discussion Paper, National Academy of Medicine, Washington, DC.
AlMani S, AlAkeel A, AlOtaibi D, et al. Dental treatment affordability and oral outcomes among U.S. adults. BMC Oral Health. 2025; 25(1):Article 542.
Hollander MJ, Kadlec H. Financial implications of the continuity of primary care. Permanente Journal. 2015 Winter;19(1):4-10.
Disclosure
This white paper was prepared by Amyn M. Amlani, PhD, in a consulting capacity (Amlani Advisory Group, LLC) for Alphaeon. Dr. Amlani is Professor and Chair, Department of Communication Sciences and Disorders at the University of Oklahoma Health Sciences Center. The analytic frameworks applied here, including the author’s previously published work on consumer decision-making in hearing care, the health-economic value of treatment, and the audiology workforce, were independently developed and exist independently of this engagement. Any reference to the role of the clinical encounter in identifying broader health concerns is limited to a non-diagnostic, referral-based view and is not a claim that treatment of hearing loss prevents cognitive or other disease. The views expressed are the author’s analytic assessment, offered to inform strategic discussion; they are not financial, legal, or clinical advice. The author’s academic research and peer-reviewed publication activity are conducted independently of this consulting relationship.

The Alphaeon ThanksGIVING Sweepstakes Is Back
Opt in by Sunday, November 1 to receive +5 bonus entries in Week 1.
Thank you for helping more patients say yes to care.
Every day, your team makes it easier for patients to move forward with the care they need, and we don't take that for granted. That's why the Alphaeon ThanksGIVING Sweepstakes is back! From November 2 through November 29, we're showing our gratitude with four weeks of Visa eGift card drawings, just for our providers.
Entering takes less than a minute, and one opt-in covers your whole practice for the entire month.
3 steps to enter
Log in to your dashboard. Go to providers.alphaeon.com and sign in.
Click "YES, Opt In My Practice." You'll see the ThanksGIVING card at the top of your dashboard. One click covers your whole practice for all four weeks.
Earn entries all November. Every application and transaction earns 1 entry. Winners are randomly selected and announced weekly.
Once you opt in, you'll see a confirmation that your practice is in, along with your store number.

Image: screenshot of the ThanksGIVING opt-in card on the provider dashboard
Opt in early for +5 bonus entries
Practices that opt in by 11:59 p.m. PT on Sunday, November 1 get 5 bonus entries in the Week 1 drawing, on top of the entries they earn that week. It's the easiest head start of the month.
4 weekly drawings, 4 chances to win
Each week is its own drawing, and every drawing awards all three prizes. Each week's drawing takes place after that week ends.
Entry week
Dates
Week 1 (+5 bonus entries for early opt-ins)
Nov 2–8
Week 2
Nov 9–15
Week 3
Nov 16–22
Week 4
Nov 23–29
Prizes every week:
Grand prize: $500 Visa eGift card
Second prize: $300 Visa eGift card
Third prize: $150 Visa eGift card
Frequently asked questions
Who at my practice can opt in? Anyone on your team with a dashboard login. One opt-in covers your entire practice, so only one person needs to do it.
Do I need to opt in every week? No. Opt in once and your practice is entered in all four weekly drawings.
What if we opt in mid-week? You won't miss anything. When you opt in partway through a week, all of your applications and transactions from that entire drawing period still count.
Do applications have to be approved to count? No. Approvals don't affect eligibility. Every Alphaeon Credit Card application submitted counts as an entry, whether or not it's approved, and so does every transaction processed.
Can my practice win more than once? No. Each practice can win one prize during the sweepstakes. Once a practice wins, it isn't eligible for later weekly drawings.
How will winners be notified? By email. Prizes are delivered electronically once the winner confirms their email address. If a winner doesn't confirm within five business days, an alternate winner may be selected.
I can't find the opt-in card. What should I do? Log in at providers.alphaeon.com and look for the ThanksGIVING card at the top of your dashboard. Still stuck? Call us at (920) 306-1794 or email teamcredit@alphaeon.com.
Weekly winners
Check back each week. We'll post the winning practices here after every drawing.
Entry week
$500 winner
$300 winner
$150 winner
Week 1 (Nov 2–8)
Coming soon
Coming soon
Coming soon
Week 2 (Nov 9–15)
Coming soon
Coming soon
Coming soon
Week 3 (Nov 16–22)
Coming soon
Coming soon
Coming soon
Week 4 (Nov 23–29)
Coming soon
Coming soon
Coming soon
Not entered yet? Log in and opt in. There's still time to win.
Official rules
1. Promotion Period
The Alphaeon ThanksGIVING Sweepstakes ("Promotion") begins at 12:00 a.m. Pacific Time (PT) on Monday, November 2, 2026, and ends at 11:59 p.m. PT on Sunday, November 29, 2026 ("Promotion Period"). The Promotion consists of four (4) weekly entry periods, each running from Monday at 12:00 a.m. PT through Sunday at 11:59 p.m. PT:
Week 1: November 2–8, 2026
Week 2: November 9–15, 2026
Week 3: November 16–22, 2026
Week 4: November 23–29, 2026
Practices may opt in at any time before or during the Promotion Period.
2. Eligibility
The Promotion is open only to enrolled Alphaeon Credit providers located in the United States who are in good standing during the Promotion Period. Practices affiliated with membership groups that do not use the Alphaeon Dashboard are not eligible to participate. Employees of Alphaeon, its affiliates, subsidiaries, advertising and promotion agencies, and their immediate family members are not eligible to participate.
3. How to Participate
Practices must opt in through the Alphaeon Dashboard at providers.alphaeon.com to participate. Any authorized member of a practice may opt in on behalf of the entire practice, and one opt-in covers all four weekly entry periods. Once a practice has opted in, entries are recorded automatically based on Alphaeon Credit Card activity:
Entry Method 1: One (1) entry for each Alphaeon Credit Card patient application submitted through the Alphaeon Dashboard. Applications count as entries regardless of approval status.
Entry Method 2: One (1) entry for each Alphaeon Credit Card transaction processed through the Alphaeon Dashboard.
A practice that opts in during a weekly entry period receives entries for all eligible activity from that entire period, beginning Monday at 12:00 a.m. PT. After each weekly entry period closes, all entries reset at 12:00 a.m. PT on Monday, giving every opted-in practice a new opportunity to earn entries for that week's drawing.
Early opt-in bonus: Practices that opt in by 11:59 p.m. PT on Sunday, November 1, 2026, receive five (5) bonus entries in the Week 1 drawing (for entries earned November 2–8, 2026).
No purchase is necessary to enter or win.
4. Prizes
Each week, three (3) winners will be selected at random from eligible entries and awarded the following prizes:
Grand Prize: $500 Visa eGift Card
Second Prize: $300 Visa eGift Card
Third Prize: $150 Visa eGift Card
A total of twelve (12) prizes will be awarded during the Promotion Period, with a total approximate retail value (ARV) of $3,800 over four (4) weeks. Limit one (1) prize per practice for the duration of the Promotion; once a practice wins, it is no longer eligible for subsequent weekly prizes.
5. Winner Selection and Notification
Winners will be selected at random from all eligible entries after each weekly entry period closes, and winners will be announced weekly.
Winners will be contacted via the email address associated with their Alphaeon Credit account and asked to confirm their preferred email address for reward delivery. Once confirmation is received, eGift Cards will be fulfilled through Tremendous, a third-party digital reward platform, and sent directly to the confirmed email address. If a winner does not confirm their email address within five (5) business days of notification, Alphaeon reserves the right to select an alternate winner.
6. General Conditions
No cash or prize substitutions are permitted except at Alphaeon's sole discretion. Alphaeon reserves the right to verify eligibility and to modify, suspend, or terminate the Promotion at any time. Taxes, if any, are the sole responsibility of each winner. Entries generated by fraud, technical failure, or unauthorized means will be void.
7. Privacy
Participant information is used solely to administer this Promotion and in accordance with Alphaeon's Privacy Policy.
8. Additional Terms
Void where prohibited by law. By participating, providers agree to these Official Rules and to Alphaeon's decisions, which are final and binding in all respects.
Questions? Call (920) 306-1794 or email teamcredit@alphaeon.com.

The Alphaeon Halloween Costume Contest Is Back!
The Alphaeon Halloween Costume Contest is back, and this year we want your whole practice in on it. Send us a photo or short video of your best costume by 7:00 PM Pacific on Wednesday, November 4, and you could win up to a $500 Visa eGift Card.
Our practices spend all year helping patients move forward with care. This is our chance to celebrate the people behind the front desk, in the treatment room, and everywhere in between. Go spooky, go silly, or go all out. A full-team theme counts as much as a solo showstopper.
The prizes
Three costumes will take home a Visa eGift Card.
Place
Prizes
1st place
$500 Visa eGift Card
2nd place
$300 Visa eGift Card
3rd place
$150 Visa eGift Card
How to enter
Entering takes about two minutes. The contest is open to all Alphaeon providers and their teams.
Snap a photo or record a short video of your costume.
Open the costume submission form.
Fill in your info and upload your photo or video.
A few tips before you submit:
Show the whole look. Make sure the full costume is clear and well lit.
Solo, group, or full team. Every format counts, so feel free to coordinate a theme.
One entry each. Only one entry per person or team is allowed.
Use the form. Only entries submitted through the form are eligible for prizes.
How we'll pick the winners
The Alphaeon team will review every entry and vote for their favorites. The three costumes with the most votes win.
Entry deadline: Wednesday, November 4, 7:00 PM Pacific
Winners announced by email
Friday, November 6
Need a costume idea?
The best entries usually come from a team that leans into a shared theme. A few starters:
Classic monster squad. Vampires, mummies, and a Frankenstein at the front desk.
Movie or TV ensemble. Pick a cast with enough roles for the whole office.
Specialty twist. A tooth fairy for dental, a "seeing double" duo for ophthalmology, or a pack of superheroes with capes for a veterinary team.
Pun night. Costumes built on a play on words always get a laugh from the judges.
Throwback decade. Pick an era and have everyone dress the part.
Get your entry in
The deadline is 7:00 PM Pacific on Wednesday, November 4. Submit your costume here.
We can't wait to see what your team comes up with. Good luck, and happy haunting!
All entries and submissions become and remain the property of Alphaeon Credit, Inc., which may use the images for marketing and advertising purposes.

Why Q4 Is the Most Strategic Time to Promote Patient Financing in Your Practice

For most dental and aesthetic practices, the fourth quarter of the year presents a convergence of patient motivators that doesn't exist at any other time — and practices that recognize this timing window and activate around it consistently outperform those that treat financing as a year-round constant without seasonal emphasis.
This isn't a general observation about the holiday season or year-end gift spending. It's a specific analysis of the financial and psychological factors that make patients uniquely likely to accept comprehensive treatment recommendations in the September through December window.
The Dental Benefits Deadline Drives Decisions
Most dental insurance plans operate on a calendar-year benefit cycle. Annual maximums — typically $1,000 to $2,000 — reset to zero on January 1st. Deductibles that have been met over the course of the year reset to zero. And the preventive visits most plans cover at 100 percent expire.
For patients who have used some of their benefit year, the math becomes compelling: the deductible is already paid, the annual maximum is still partially or fully available, and treatment completed before December 31st captures insurance contribution that will simply disappear in 47 days if it doesn't.
This creates natural patient motivation to move forward with treatment they've been considering — but only for patients who can actually fund the out-of-pocket remainder. Patient financing closes exactly this gap. The patient who is newly motivated by the benefit deadline but can't cover the patient portion becomes the patient who says yes to treatment when financing is offered as the standard path.
Practices that proactively raise the benefit deadline conversation at every fourth-quarter appointment — "Before we look at your treatment options, I want to mention that your benefit year resets January 1st, and we have options to help you cover the patient portion today" — capture treatment acceptance that a reactive approach consistently leaves behind.
The FSA Deadline Adds Urgency
Flexible Spending Account funds are typically use-it-or-lose-it by December 31st. A patient who contributed the maximum to their FSA in January — up to $3,200 in 2026 for self-only coverage — and has not yet spent that balance is holding pre-tax dollars with a hard expiration date.
Dental treatment is FSA-eligible, including many cosmetic procedures when performed in a clinical context. A patient with $800 remaining in their FSA who also needs $1,200 in recommended treatment has most of their cost covered — if they know to ask and if the conversation happens at the appointment.
Many patients are entirely unaware of how much FSA balance they have or when it expires. Practices whose front desk teams routinely ask "do you have an FSA or HSA you'd like to apply to today's treatment?" capture treatment decisions that never happen at practices where the question isn't asked.
Patient Psychology in Q4 Shifts Toward Action
The fourth quarter produces a specific motivational shift: the awareness that the year is ending creates a natural deadline psychology. Goals that have been deferred — the dental work that's been on the radar since February, the cosmetic treatment that's been "something to do eventually" — become more salient when the year is running out.
Patients are simultaneously processing holiday and social events where their appearance and health are front of mind. The smile that's been a background concern becomes more immediate when the family reunion or the holiday party is on the calendar.
This convergence of financial motivation (use your benefits before December 31st) and social motivation (look and feel your best for upcoming events) represents the highest patient receptivity to comprehensive treatment of any quarter. Practices that activate their case presentation and financing conversation around this dynamic — rather than treating Q4 as just another quarter — see measurably higher treatment acceptance rates.
How Alphaeon Credit Positions Your Practice to Capture Q4 Momentum
Alphaeon Credit provides practices with patient financing tools specifically designed to integrate naturally into the clinical conversation. When financing is presented as the standard option — "we typically discuss how patients want to handle the portion that insurance doesn't cover; Alphaeon Credit is what most of our patients use" — utilization rates are significantly higher than when financing is only offered after patients express financial concern.
The Q4 activation strategy that consistently drives results:
Identify patients with upcoming appointments who have used some but not all of their annual maximum. Brief those patients by email or phone before the appointment: "Before your visit, we wanted to let you know your benefit year ends December 31st — if there's treatment we've discussed that you'd like to address this year, this is a great time to move forward. We have same-day financing options that make it easy." Patients who arrive at the appointment already primed for the financing conversation accept it at dramatically higher rates.
Alphaeon Credit's application process takes minutes, decisions are typically immediate, and the provider portal is designed for same-day treatment authorization. The administrative friction that might cause a patient to defer a decision is removed.
Set Up for Q4 Before October
Practices that see the best fourth-quarter results begin their Q4 activation in September — before the month-end urgency that October and November produce. The practice that reaches out to benefit-year patients in September has two to three months of treatment capacity to fill. The practice that starts the conversation in November is competing with a compressed schedule.
Visit myalphaeoncredit.com to learn more about integrating Alphaeon Credit into your Q4 strategy, or contact the Alphaeon provider team for practice-specific guidance on benefit-year conversation scripts and patient communication materials. The patients who want your recommended treatment are in your schedule right now — the question is whether the right conversation happens at their appointment.
The Enrollment Investment
Practices that haven't yet added Alphaeon Credit as a financing option sometimes assume the setup process is a barrier. It isn't. Enrollment takes less than five minutes, there are no enrollment fees, and same-day applications are available from the first day of participation. The ROI on the first financed comprehensive case covers the administrative investment many times over.
For practices already offering other financing options alongside Alphaeon Credit, the comparative approval rates and credit lines that Alphaeon offers — designed specifically for aesthetic and dental procedures with higher per-case costs — often capture patients who weren't approved through other financing products.
Visit myalphaeoncredit.com to begin the enrollment process or to learn more about practice support resources including conversation guides and patient communication materials. Q4 starts now.

Fear, Finances & Follow-Up: The 3 Biggest Factors Impacting Elective Procedure Conversion
Why do patients who want a procedure still hesitate to move forward?
The answer often comes down to three things: Fear. Finances. Follow-up.
Join us September 28th at 1 PM CST for a practical conversation with Dallas Logan, COO & Practice Administrator, exploring what happens between patient interest and a confident decision to move forward.
We’ll dig into how practices can:
•• Recognize the emotional barriers patients may not openly express
•• Discuss affordability in a way that builds trust—not pressure
•• Create stronger follow-up after the consultation
•• Better support patients throughout the decision-making process
If you work in vision, aesthetics, cosmetic surgery, or elective care, this is a conversation you won’t want to miss.
📅 Today | September 28
⏰ 1 PM CST
Register and join us → https://lnkd.in/gKuNefEv

Best Patient Financing Options for Dental Practices: What Dentists Should Compare in 2026
When cost gets in the way of care, the right patient financing solution can make a meaningful difference.
For dental practices, patient financing isn't simply another payment method. It can help patients move forward with recommended treatment, improve case acceptance, and give teams more ways to address affordability without immediately discounting care.
But not all patient financing platforms work the same way.
If you're comparing patient financing for your dental practice, here are the most important factors to consider—and some of the leading options available today.
What Should Dentists Look for in Patient Financing?
Before choosing a financing partner, look beyond brand recognition. Consider how the program performs for both your patients and your practice.
1. Approval Rates
A financing program only helps if your patients can actually qualify.
Ask potential partners about their approval performance and whether they can serve patients across a broad range of credit profiles.
Higher approval potential can mean more patients have an opportunity to move forward with recommended treatment.
2. Patient Financing Options
Different patients need different ways to pay.
Look for a financing solution that provides multiple payment options, competitive terms, and enough flexibility to accommodate everything from routine dental procedures to larger treatment plans.
3. Credit Limits
For higher-value procedures such as implants, cosmetic dentistry, orthodontics, or full-mouth treatment, available credit matters.
A higher credit line can help prevent patients from having to piece together multiple payment methods to complete treatment.
4. Cost to the Practice
Merchant fees can vary significantly between financing programs—and promotional financing offers can sometimes carry higher provider costs.
Compare the total economics of each program, not just the patient-facing promotion.
The right financing partner should help you increase access to care without unnecessarily giving away practice revenue.
5. Patient Experience
Applying for financing shouldn't create another obstacle.
Look for a simple digital application, fast decisions, transparent offers, and an experience your team can comfortably introduce to patients.
6. Practice Support
Technology matters. So does having someone to call.
Consider the level of provider support, training, implementation assistance, reporting, and ongoing account management included with the program.
Your financing partner should help your team use the program successfully—not simply give you access to a portal.
Leading Patient Financing Options for Dentists
Several established platforms serve dental practices. The best choice will depend on your patient population, treatment mix, average case size, and practice goals.
Alphaeon Patient Financing
Best for: Dental practices looking to increase financing access while balancing patient offers and practice economics.
Alphaeon Patient Financing is designed to help healthcare providers give more patients a way to move forward with care.
For dental practices, Alphaeon offers flexible patient financing options while focusing on the factors that matter to providers: approvals, patient offers, competitive merchant fees, and provider support.
Alphaeon's financing solutions can support a wide range of dental treatment—from everyday procedures to larger treatment plans.
Why dental practices consider Alphaeon:
Competitive approval rates
Flexible patient financing options
Competitive merchant fees
Financing for a wide range of treatment amounts
Simple patient application experience
Dedicated provider support
No cost to enroll
Learn more about Alphaeon Patient Financing →
CareCredit
Best for: Practices prioritizing consumer familiarity and an established healthcare credit card.
CareCredit is one of the most recognized names in healthcare financing and is accepted across a large network of healthcare providers.
Its healthcare credit card can be used for eligible dental expenses and offers promotional financing options depending on the provider and transaction.
CareCredit may be attractive to practices that value strong consumer awareness or already see patients carrying the card.
Sunbit
Best for: Practices prioritizing a quick application and point-of-sale financing experience.
Sunbit offers financing across dental and other service industries, with an emphasis on a streamlined application experience and broad consumer approval.
For practices evaluating financing solutions, Sunbit is worth comparing on approval performance, available patient terms, merchant costs, and treatment amount limits.
Cherry
Best for: Practices interested in a buy-now-pay-later style financing option.
Cherry has grown within dental, aesthetics, and other healthcare categories by offering patients installment payment options through a relatively simple digital experience.
Practices should compare available terms, approval reach, provider fees, and maximum financing amounts against other options.
Proceed Finance
Best for: Practices with high-value treatment plans.
Proceed Finance focuses heavily on financing larger healthcare and dental procedures.
For practices performing implants, full-arch dentistry, or other high-ticket procedures, longer repayment periods may make Proceed worth considering as part of a broader financing strategy.
Which Patient Financing Company Is Best for Dentists?
There isn't one financing platform that's right for every dental practice.
Instead, ask a better question:
Which financing solution gives more of my patients a realistic way to say yes to treatment—while still making financial sense for my practice?
When comparing Alphaeon, CareCredit, Sunbit, Cherry, Proceed Finance, or another financing provider, evaluate:
CompareQuestions to AskApprovalsHow many of my patients are likely to receive an offer?Patient termsAre there multiple financing options and payment structures?Credit availabilityCan the program support my typical treatment amounts?Practice feesWhat will financing actually cost my practice?Patient experienceHow easy is it to apply and understand available options?Provider experienceWhat support and training will my team receive?Case acceptanceDoes the program help remove affordability barriers at the point of treatment?
Consider Offering More Than One Financing Option
For many dental practices, the answer doesn't have to be choosing one financing company.
Patients have different financial situations and credit profiles. A financing option that works well for one patient may not work for another.
Giving your team access to multiple financing solutions can provide another path when a patient can't move forward with their first option.
The objective isn't financing for financing's sake.
It's giving more patients a way to access the care you've already recommended.
See What Alphaeon Could Mean for Your Practice
If you're evaluating patient financing—or wondering whether your current financing program is leaving approvals and treatment starts on the table—it's worth comparing your options.
Alphaeon Patient Financing helps dental practices expand access to care with competitive approvals, flexible financing options, competitive merchant fees, and dedicated provider support.
See how much more opportunity your practice could capture.

Why Patients Who Finance Spend More — and What the Numbers Mean for Your Practice

There's a version of the patient financing conversation that frames it as a courtesy — something you offer for patients who need help affording treatment. That framing undersells what the data actually shows.
Patients who finance don't just afford more. They choose more. They accept comprehensive treatment plans at higher rates, return for additional services, and generate meaningfully higher average transaction values than patients paying entirely out of pocket. The financing offer isn't just a payment accommodation — it's the mechanism that converts "I'll think about it" into "when can we start?"
Alphaeon Credit has been working with healthcare providers across aesthetic, dental, vision, dermatology, medspa, and audiology practices for over a decade. With more than 12,500 provider partners nationwide and billions in financed procedures, the patterns in the data are not subtle.
The Case Acceptance Gap Is Significant — and Predictable
Patient financing affects case acceptance at every practice size and in every specialty that offers it. The pattern is consistent: when patients have a clear, accessible path to paying for recommended treatment, the percentage who move forward with that treatment increases meaningfully.
Among practices that have integrated Alphaeon's financing platform, providers report increases in case acceptance rates that translate directly to practice revenue. Partners in aesthetic and cosmetic practices have experienced revenue increases of up to 64% after implementing structured patient financing. Practices that were previously relying entirely on cash and credit card payments consistently find that a meaningful segment of patients who previously hesitated or declined were not declining treatment — they were declining uncertainty about payment.
The difference is worth internalizing: a patient who says "I need to think about it" or "let me talk to my spouse" is often not uncertain about wanting the treatment. They're uncertain about how they're going to pay for it. The financing conversation, when it happens early in the treatment planning process, resolves that uncertainty before it becomes a lost case.
Patients Who Finance Accept More Comprehensive Treatment
This is the piece of the financing equation that practices most consistently underestimate. The patient who might have accepted one procedure with a cash or card payment is significantly more likely to accept a comprehensive treatment plan when monthly payment options are available — because the question shifts from "can I afford $X today" to "can I afford $Y per month."
The difference between those two questions is enormous for the average patient's decision-making. A $4,000 treatment plan that requires payment in full is a significant one-time financial commitment that many patients struggle to approve in the moment. That same treatment plan presented as $120 to $180 per month enters a completely different mental framework — one where it competes with other monthly expenditures rather than with savings or emergency funds.
The result: patients who finance are more likely to agree to the full scope of recommended treatment rather than selecting one component and deferring the rest. For practices where comprehensive treatment plans represent a significant portion of revenue — cosmetic dental practices, aesthetic medicine, vision correction — this difference in treatment acceptance scope is one of the highest-leverage factors in practice financial performance.
Alphaeon offers credit lines up to $25,000, which covers the full cost of most elective treatment plans in the specialties it serves, including high-value cosmetic surgery procedures, comprehensive orthodontic cases, and multi-procedure aesthetic treatment plans.
Higher Approval Rates Mean More Patients Move Forward
Not all patient financing platforms are equal in their approval capabilities, and the approval rate matters as much as the offer itself. A financing platform that declines a significant percentage of applicants doesn't solve the case acceptance problem — it creates a new source of patient disappointment and staff awkwardness.
Alphaeon's multi-tier financing structure is specifically designed to approve patients across a wider credit spectrum than single-tier platforms typically achieve. Patients who might not qualify for the lowest promotional rates can be offered alternative terms that still allow them to move forward with treatment. The result is a higher overall approval rate — meaning more of the patients who want to finance actually can.
Practices that have switched to Alphaeon from other financing partners consistently report that approval rates are higher and credit limits are more generous, allowing patients to add procedures rather than trim their treatment scope to fit a lower credit limit.
The application itself takes less than five minutes and uses a soft credit inquiry — meaning patients can explore their options without any impact on their credit score. This removes one of the most common hesitations patients have about applying: the fear that checking their financing options will hurt their credit.
The Operational Side: Why Staff Adoption Matters
The best patient financing platform doesn't generate results if it isn't used consistently. One of the most common failure modes for practice financing programs is that staff introduce it only for patients who explicitly ask about payment options — rather than offering it proactively as part of every treatment plan conversation.
Practices where financing is presented as a standard option — "we typically discuss payment options at this point; Alphaeon Credit is what most of our patients use" — see substantially higher utilization than practices where it's only mentioned when patients express financial concern. Patients who might have declined to ask about financing out of embarrassment accept it readily when it's framed as the standard practice approach.
Alphaeon provides ready-to-use conversation guides and onboarding support specifically to help practices integrate financing conversations naturally into their existing workflow. The setup process takes less than five minutes to enroll, and the provider portal is designed to make same-day applications straightforward for front desk and treatment coordinator staff.
What the Numbers Add Up To
The practices that perform best with patient financing share a few characteristics: they offer it consistently, they present it early in the treatment conversation, and they use a platform with high approval rates and flexible terms. The arithmetic is straightforward — a practice that converts an additional 10 to 20% of previously-declining treatment plans into accepted cases is compounding that revenue across every provider on staff, every day.
Alphaeon Credit is backed by Comenity Capital Bank, one of the largest card issuers in the country, providing the financial stability and regulatory compliance that both practices and patients expect from a healthcare financing partner. With over a decade of experience in the healthcare financing space and a dedicated practice support hotline staffed with people who answer the phone, the platform is built to be a genuine operational asset — not just a payment option.
Partner With Alphaeon Credit to Grow Practice Revenue
Alphaeon Credit works with aesthetic and plastic surgery practices, dental offices, orthodontic practices, medical spas, dermatology practices, audiology clinics, ophthalmology practices, and more. Enrollment takes five minutes. Onboarding support is personalized. And the outcome data across 12,500+ provider partners makes the case clearly.
Visit myalphaeoncredit.com to learn more or begin the enrollment process. The patients who want your recommended treatment are already in your practice — Alphaeon helps more of them say yes.

The Psychology of Patient Decision-Making: Understand What Influences Treatment Choices
Dr. Anum Chaudhary brings an unusual combination of clinical dentistry, neuroscience, and behavioral psychology to the patient experience.
A practicing dentist with Envisage Dental in the UK, Dr. Chaudhary has built her work around understanding the connection between the brain, behavior, communication, and dentistry. She is the founder of The Neurodentist and an NLP Practitioner, and her educational work explores subjects ranging from stress and the mouth-brain connection to behavioral psychology in the dental chair.
Her perspective comes from both sides of the treatment conversation: understanding the clinical recommendation as a dentist while studying the behavioral forces influencing the person sitting in the chair.
That makes this conversation particularly relevant for dentists, treatment coordinators, practice leaders, and anyone responsible for helping patients understand and move forward with recommended care.
The Big Idea
Patients don't make healthcare decisions based on clinical information alone.
Understanding how people make those decisions can change the way your team communicates, builds trust, responds to hesitation, and ultimately creates a better patient experience.
Join Alphaeon and Dr. Anum Chaudhary for a different kind of conversation about case acceptance—one that starts with understanding the patient.

The Affordability Advantage: Turning Patient Financing Into Practice Growth
Featuring Nick Sideris, Co-Founder of EyeAdvisor & Patient Pipeline
Getting patients interested in a procedure is hard enough.
Losing them at the finish line because of cost is harder.
For many practices, affordability is still treated like the last part of the conversation—something to address after a patient hesitates. But by then, you may have already lost momentum.
What if affordability became part of your growth strategy instead?
Join Nick Sideris, co-founder of EyeAdvisor and Patient Pipeline, for a practical conversation about how practices can use patient financing to help more patients move from interested to scheduled—without making the experience feel like a sales pitch.
Nick has spent more than 15 years working in ophthalmology marketing and strategy, helping surgeons and practice leaders close the gap between clinical recommendations and premium patient outcomes. He knows where patient interest gets lost—and what practices can do differently.
The big idea:
You don’t always need more leads. You need more of the patients you already have to feel confident saying yes.
That’s where affordability can become an advantage.
Join us for a straightforward conversation about making patient financing work harder for your patients—and your practice.
Save your seat and register here.

Beyond the Cleaning: Connecting Hygiene, Patient Care & Practice Growth with Misty Mattingly
The hygiene chair does a lot more than prevent problems.
It’s where relationships are built.
Where changes in oral health are discovered. Where treatment conversations often begin. And where some of the biggest opportunities to improve patient care can start.
Join Misty Mattingly, RDH, BS, FADHA, Chief of Dental Hygiene Operations at Sage Dental, for an important conversation.
We’ll explore how practices can better connect hygiene to the bigger picture—from stronger patient relationships and treatment follow-through to case acceptance and overall practice performance.
At Alphaeon, we believe supporting providers means doing more than offering financing. It means bringing together smart voices, practical ideas, and conversations that help practices get better.
About the Presenter
Misty Mattingly RDH, Chief of Dental Hygiene Operations, Sage Dental
With 28 years of experience in dentistry, Misty Mattingly is a dynamic clinical leader who makes learning fun while delivering exceptional results. As the Chief of Dental Hygiene Operations for Sage Dental and past president of the GDHA, Misty has received numerous awards including the 2023 Women in DSO – Clinical Leadership award. She champions individual growth and collective success in a fun, supportive environment geared towards shared success.

The Partial Yes Problem: How Patient Financing Unlocks Comprehensive Treatment Acceptance

There is a conversion metric most practices track carefully, and a revenue metric most practices don't track nearly carefully enough.
The metric practices watch is case acceptance rate — the percentage of recommended treatments that patients agree to proceed with. The metric most practices underestimate is treatment plan completeness — the percentage of recommended treatment that patients actually say yes to versus the portion they defer, decline, or agree to address "later."
These are different problems. A practice can have a respectable case acceptance rate and still be leaving substantial production on the table every week — because patients are accepting some of what's recommended but systematically declining the rest. The dental patient who agrees to the two fillings but defers the implant. The cosmetic patient who books the consultation but commits only to injectables when a comprehensive skin rejuvenation plan was presented. The vision patient who chooses the basic procedure option when the premium option was clinically the better choice.
This is the partial yes problem. And in the majority of cases, the root cause is financial — not clinical disagreement, not distrust of the provider, not indifference to the recommendation. The patient likes the treatment plan. They simply can't see how to pay for all of it at once.
Why Partial Acceptance Is a Revenue Problem That Compounds
When a patient accepts part of a treatment plan and defers the rest, several things happen — and none of them are good for the practice.
The deferred treatment requires a second scheduling cycle, a second clinical review, and the administrative overhead of a new treatment coordination conversation. Some percentage of patients who defer don't return — not because they changed their mind about the treatment, but because life intervenes and the path of least resistance is inaction. For the patients who do return, the treatment that seemed straightforward at the original consultation may have progressed in the interval, creating a more complex case that takes longer and produces more friction than the original plan would have.
There is also a patient experience dimension. A patient who wanted a comprehensive result but received a partial one because financial reality narrowed what they could agree to often carries a nagging awareness that they didn't quite get to the outcome they were hoping for. That awareness affects satisfaction scores, referral behavior, and the likelihood of accepting future treatment recommendations.
The revenue lost to partial acceptance isn't dramatic and visible the way a cancelled procedure is. It disappears quietly, case by case, in the gap between what was presented and what was accepted. Aggregated across a summer of high-volume consultations, it becomes significant.
How Financing Changes the Calculation
Patient financing transforms the treatment plan conversation in a specific and powerful way: it separates the question of what the patient wants from the question of what the patient can pay for in a lump sum right now. These are different questions, and conflating them is the mechanism by which partial acceptance happens.
When a provider presents a comprehensive treatment plan and a financing option simultaneously — rather than waiting for the patient to hesitate at the price — the patient can evaluate the full recommendation on its clinical merits. Their decision about what to accept becomes about what they want to do for their health, their appearance, or their quality of life, not about what's manageable to write a check for today. A monthly payment frame — particularly with promotional financing options that make a comprehensive plan look similar in monthly terms to a partial one — changes which option feels achievable.
This is the mechanism behind a finding Alphaeon observes across its provider network: practices that present financing proactively at the point of treatment planning — rather than reactively after a patient objects to cost — see higher average production per accepted case than practices where financing is offered as a fallback. They're not converting more patients. They're converting more of each patient's recommended treatment plan.
The Comprehensive Case vs. the Partial Case: A Production Math Example
Consider a dental practice presenting a treatment plan that includes a crown, two fillings, and a dental implant for a total of $4,800. The patient with no financing pathway mentally separates the plan into what feels urgent and what can wait. They accept the crown and the fillings at $1,400 and defer the implant.
The practice has a technically successful consultation. The patient said yes. The case acceptance is logged.
But $3,400 in recommended production just walked out the door, scheduled into an uncertain future appointment that may or may not happen. Over the course of a week with fifteen such consultations, the partial acceptance pattern across even a fraction of those cases adds up to production that exists in theory — in the treatment plans — but not in the schedule.
When the same treatment coordinator presents the $4,800 plan alongside a monthly payment option of approximately $140 per month on a promotional financing plan, the conversation changes. The implant is no longer an abstract future expense — it's a specific, manageable addition to the monthly payment the patient is already mentally computing. The comprehensive plan becomes achievable. The treatment the patient actually needed gets scheduled.
Presenting Financing Alongside the Full Plan — Not After the Objection
The timing of the financing conversation determines its effectiveness more than almost any other variable. When practices present financing as a recovery mechanism — something offered after a patient objects to cost or asks about payment options — it arrives in the context of hesitation, which frames it as a consolation rather than a tool. The patient has already mentally begun to downscale what they'll accept.
When practices present financing at the same moment the full treatment plan is presented — as a natural part of the treatment coordinator's standard conversation — patients evaluate the full plan and the payment option simultaneously, before narrowing has occurred. The Alphaeon platform is specifically designed to support this workflow: applications take under five minutes, approvals are same-day in most cases, and the soft inquiry that checks eligibility produces no credit score impact, which removes the last piece of friction from presenting the option early.
Training front desk and treatment coordinator staff to introduce Alphaeon at the plan presentation stage — rather than waiting for the patient to raise the cost question — is the single highest-leverage change most practices can make to address the partial acceptance problem.
Measure What You're Missing
If your practice isn't currently tracking the gap between recommended treatment value and accepted treatment value by patient, the partial yes problem is almost certainly invisible in your production metrics. It doesn't show up as a lost case. It shows up as a slightly lower production number than your consultation volume would predict.
Alphaeon's dedicated practice support team works with providers specifically to identify where partial acceptance is occurring, how the financing conversation is currently being positioned in the treatment planning workflow, and what changes in presentation timing and language produce measurable improvement in full-plan acceptance rates.
The cases are already in your schedule. The treatment plans are already being presented. The question is how much of each plan you're actually capturing.
Make the Full Treatment Plan Achievable
Visit myalphaeoncredit.com/get-started to enroll, access training resources, and connect with a dedicated practice support specialist. Enrollment is free — no application fees, no monthly fees, no cost for marketing materials. Your patients want the comprehensive plan. Give your team the tool to make it possible. Call (949) 284-4507 or visit myalphaeoncredit.com to get started today.

The Financing Conversation: 5 Mistakes That Can Keep Patients From Moving Forward
A patient can be ready for care, understand its value, and trust your practice—and still walk away without scheduling.
Often, the turning point is when the conversation shifts to cost.
A significant out-of-pocket expense introduces new questions: Can I afford this right now? Should I wait? Is there another way to pay?
Patient financing can help bridge the gap between wanting to move forward and being financially ready to do so. But simply offering financing isn't enough. How and when payment options are presented matters.
Here are five common mistakes practices make—and how to create a better financing conversation.
Mistake #1: Waiting Until the Patient Hesitates
One of the most common mistakes is treating financing as a solution to an objection rather than a standard payment option.
The practice presents the recommended care or service and total cost. The patient hesitates. Only then does someone say, "We also offer financing if you need it."
By this point, the patient may already be experiencing sticker shock, and financing can feel like something offered only because they can't afford to move forward.
Instead, introduce payment flexibility naturally:
"The total cost is $4,500. We have several ways you can pay, including financing options that allow eligible patients to spread the cost over time."
Now financing isn't a rescue plan. It's simply another way to pay.
Mistake #2: Assuming You Know Who Needs Financing
Appearances don't tell you how someone wants to manage their money.
A patient with a high income may prefer monthly payments. Someone who could pay the full balance may not want to use thousands of dollars in available cash at once. Others may have financial priorities your team knows nothing about.
When staff selectively offer financing based on who they believe "needs" it, they make a financial decision for the patient.
Instead, present available payment options consistently and allow patients to decide what works for them.
The goal isn't to convince every patient to finance. It's to make sure every patient understands their options.
Mistake #3: Focusing Only on the Total Price
When a patient is presented with a cost of $3,000, $5,000, or $10,000, the immediate question often becomes: "Do I have that much available right now?"
Financing gives eligible patients another way to consider the expense: payments over time rather than the entire cost upfront.
Instead of simply asking:
"How would you like to pay the $5,000?"
Consider:
"Your total cost is $5,000. We can also explore financing options if you'd prefer to pay over time."
The total cost should always be clear. It just doesn't have to be the end of the affordability conversation.
Mistake #4: Treating Financing Like a Last Resort
Patients are accustomed to having choices in how they pay for significant expenses. Yet financing is sometimes presented cautiously or only after other payment methods have been exhausted.
The language your team uses matters.
"Do you need financing?" puts the focus on financial need.
"Would you like to explore your payment options?" puts the focus on choice.
That shift helps normalize financing as an available payment method rather than something reserved for patients experiencing financial difficulty.
Practices can reinforce this by making financing visible throughout the patient journey—from the website and appointment materials to consultations and in-office signage.
Mistake #5: Expecting Your Team to Explain Something They Don't Fully Understand
Even the best financing program won't help if your team isn't comfortable talking about it.
Patients will have questions about how the application works, what happens after approval, and what payment options may be available. If staff aren't confident answering basic questions, they're less likely to introduce financing naturally.
Every patient-facing team member doesn't need to be a financing expert. But they should understand the basic process, know how to introduce payment options, and know where to direct patients for additional help.
Consider incorporating financing into new-hire onboarding and periodically reviewing it with existing staff. Even practicing a few common patient conversations can help teams discuss cost more confidently.
Make Financing Part of the Patient Experience
The strongest financing conversations often don't feel like financing conversations at all. They're simply part of helping patients understand their options.
The patient understands the recommended care or service and its benefits. Your team explains the cost and available ways to pay. The patient decides what works best for them.
No assumptions. No waiting for the patient to admit that cost is a concern.
When payment flexibility becomes a standard part of the patient experience, practices can remove unnecessary friction at one of the most important points in the patient journey.
Creating More Paths Forward
No single financing option will work for every patient. Credit profiles, costs, and financial circumstances vary, which is why having options that serve a broader range of patients can be valuable.
Alphaeon Credit provides financing for qualified patients with credit lines up to $25,000 and a variety of promotional and extended payment options. For patients who may not qualify through Alphaeon Credit, Alphaeon Access provides an additional financing pathway, helping practices serve patients across a broader credit spectrum.
Together, these options can help make financing a more consistent part of the conversation without deciding in advance what a patient can or cannot afford.
Ultimately, the goal is simple: clearly communicate the value, clearly present the payment options, and give each patient the opportunity to decide what works best for them.

RCM Education for Executive Leadership: What Every CEO, CFO, and COO Needs to Know About Revenue Cycle
Join us for an executive-level webinar featuring Cissy Mangrum, MBA, CMPE, CPC, CDC, nationally recognized healthcare operations strategist and revenue cycle authority, as she shares what every CEO, CFO, and COO needs to know about revenue cycle—but was never told.
Revenue cycle is no longer just an operational function.
Webinar Event
July 9, 2026
3:30 PM CDT
In today's healthcare environment, it's a strategic growth driver—and one of the biggest blind spots for executive leadership.
As patient financial responsibility continues to rise, many organizations are making critical business decisions without full visibility into where revenue is leaking, where patients are falling out of the process, and how financial friction is impacting growth.
Join us for an executive-level webinar featuring Cissy Mangrum, MBA, CMPE, CPC, CDC, nationally recognized healthcare operations strategist and revenue cycle authority, as she shares what every CEO, CFO, and COO needs to know about revenue cycle—but was never told.
What You'll Learn
Where revenue is leaking—and why it's often invisible at the executive level
How rising patient responsibility is changing the economics of care
Why traditional revenue cycle metrics don't tell the full story
What high-performing organizations are doing differently to improve cash flow, patient experience, and sustainable growth
Meet the Speaker
With more than 25 years of experience and having worked alongside 2,700+ physicians and healthcare providers, Cissy Mangrum, Co-Founder and Chief RCM Officer at RevTech Partners, has helped organizations optimize operations, improve financial performance, and create exceptional patient experiences. Cissy is known for helping healthcare leaders uncover hidden opportunities within their revenue cycle that drive measurable business growth.

The Hidden Revenue Already in Your Practice: Reactivating Patients Who Said "Not Yet"

Every practice has them—folders full of consultations that never converted. Patients who seemed genuinely interested, who asked thoughtful questions, who left saying they'd "think about it" or "call back soon." Weeks became months. Months became years. Those patients represent procedures that were wanted but never scheduled, treatment plans that were presented but never accepted, revenue that was almost captured but ultimately lost.
Most practices treat these unconverted consultations as closed files. The patient said no, and that's that. But here's what a decade of working with healthcare practices has taught the team at Alphaeon Credit: most of those patients didn't actually say no. They said "not yet." And "not yet" is a very different answer—one that often converts to "yes" when the circumstances change.
Understanding Why Patients Delay
Before attempting to reactivate past consultations, it helps to understand why patients delay in the first place. The reasons fall into several categories, and each suggests a different reactivation approach.
Financial timing was wrong. The patient wanted the treatment but couldn't fit it into their budget at that moment. Maybe they'd just paid holiday expenses, covered an unexpected car repair, or hadn't yet received their tax refund. The desire was real; the timing wasn't. These patients are often excellent reactivation candidates because their underlying interest hasn't changed—only their financial circumstances have.
They needed time to decide. Some patients genuinely need to process major decisions, especially for elective procedures with significant costs. What felt overwhelming at the consultation may feel more manageable after reflection. The patient who left uncertain may now feel ready—but won't reach out unless prompted.
Life got in the way. A family emergency, a job change, a health issue, or simply the chaos of daily life pushed the procedure off the priority list. These patients often still want the treatment and feel guilty about not following through. A well-timed, non-judgmental outreach can move them back toward action.
They found the cost barrier insurmountable. If financing wasn't presented effectively—or wasn't presented at all—patients may have concluded they simply couldn't afford the procedure. They left believing the door was closed when it actually wasn't.
The Cost of Ignoring Past Consultations
Practices invest significantly in generating new patient consultations. Marketing, advertising, referral programs, community presence, online reputation management—all of these efforts aim to get prospective patients through the door. When those consultations don't convert, that investment yields no return.
But the cost goes beyond wasted marketing dollars. Every unconverted consultation represents:
The time clinicians spent evaluating the patient and developing treatment plans
The administrative time spent scheduling, confirming, and documenting the visit
The opportunity cost of that appointment slot, which could have held a converting patient
The potential lifetime value of a patient relationship that never developed
When practices successfully reactivate even a fraction of past consultations, the return on that effort is remarkably high. These patients require no new marketing spend. They've already been evaluated. Treatment plans already exist. The heavy lifting is done—all that remains is removing whatever barrier prevented them from proceeding.
Building a Reactivation System
Effective reactivation isn't about making one desperate phone call to old contacts. It requires a systematic approach that respects patients while creating genuine opportunities for reconnection.
Start with segmentation. Not every past consultation deserves the same approach. Patients who consulted last month are different from those who consulted two years ago. Patients who expressed strong interest but cited cost concerns are different from those who seemed ambivalent about the treatment itself. Segment your unconverted consultations by recency, stated reason for delay, treatment type, and any other relevant factors.
Lead with value, not sales pressure. The worst reactivation approach is a message that essentially says "you didn't buy from us before, please buy now." Instead, lead with something genuinely useful. Has something changed that's relevant to their situation? New technology? New financing options? New research supporting the procedure they considered? Give them a reason to re-engage beyond just "we want your business."
Make it easy to restart. Patients who delayed once may feel awkward about returning. They might worry about judgment, about having to re-explain their situation, about starting the whole process over. Assure them that their records are on file, that they're welcome back whenever they're ready, and that the path forward is simple.
Present financing proactively. If cost was a barrier—stated or suspected—the reactivation message should address it directly. "We now offer flexible financing options that make treatment more accessible" or "Many patients are surprised to learn they can begin treatment for monthly payments that fit their budget" opens doors that patients may have assumed were closed.
The Financing Conversation, Take Two
For patients whose original consultation predates your practice's current financing offerings—or whose experience didn't include a strong financing presentation—reactivation provides a second chance to have that conversation correctly.
This is particularly relevant for practices that have upgraded their financing programs. If you previously offered single-tier financing that declined patients with less-than-perfect credit, and you now offer multi-tier options with broader approval, those previously declined patients deserve to know. The patient who was told "no" two years ago may receive a "yes" today.
Even patients who weren't formally declined may benefit from a refreshed financing conversation. Perhaps financing was mentioned but not emphasized. Perhaps monthly payment options weren't calculated specifically for their treatment plan. Perhaps they didn't realize how accessible their desired treatment could be.
Reactivation outreach that specifically highlights financing—"We're reaching out because we've expanded our payment options and wanted to make sure you knew about them"—addresses cost barriers directly while giving patients a face-saving reason to reconsider.
Timing Reactivation Strategically
Certain moments create natural opportunities for reactivation outreach.
After major financial events. Tax season, bonus seasons, and the start of new insurance years create windows when patients may have more financial flexibility or motivation to use benefits before they expire.
When something changes at your practice. New technology, new providers, new services, expanded hours, or new financing options all provide legitimate reasons to reach out. "We wanted to let you know about some changes that might be relevant to the treatment we discussed" feels helpful rather than pushy.
At natural decision points. The approach of a new year prompts reflection and resolution-making. Patients who've been putting off treatment may be more receptive to outreach in late fall or early winter.
Before life milestones. If you know a patient was considering treatment before a specific event—a wedding, reunion, major birthday—outreach that references adequate lead time can be effective. "We know you mentioned wanting to address this before your daughter's wedding, and we wanted to reach out with enough time to ensure you'd be completely healed."
What Reactivation Messages Should Include
Effective reactivation outreach includes several key elements:
Acknowledgment of time passed. Don't pretend the gap didn't happen. A simple "It's been a while since we last spoke" acknowledges reality and avoids awkwardness.
No guilt or pressure. Patients delayed for their own reasons. Making them feel bad about it guarantees they won't respond. Keep the tone warm and welcoming.
A reason for reaching out. Give them something specific—new options, relevant timing, an update they'd want to know about. Random "just checking in" messages feel like sales calls.
Easy next steps. Tell them exactly what to do if interested. Call this number, reply to this email, click this link. Remove all friction from re-engagement.
Financing information when appropriate. If cost was a known or likely barrier, address it explicitly. Let them know affordable options exist.
Measuring Reactivation Success
Track reactivation efforts separately from general marketing to understand their true return. Relevant metrics include:
Response rate to reactivation outreach
Consultation reconversion rate (reactivated patients who schedule follow-up)
Procedure completion rate among reactivated patients
Average case value of reactivated patients
Cost per reactivated case (typically minimal compared to new patient acquisition)
Most practices find that reactivated patients convert at higher rates and require lower investment than entirely new prospects. This makes reactivation one of the most efficient revenue-generating activities a practice can undertake.
Start Recovering Lost Revenue Today
Your practice already has a database of patients who wanted treatment but didn't proceed. That database represents real revenue waiting to be recovered—revenue that requires no new marketing spend, no new consultations, and minimal administrative effort.
Alphaeon Credit helps practices not only convert new consultations but also reactivate past ones. With multi-tier financing that approves patients across the credit spectrum, competitive terms that make treatment accessible, and staff training resources that help teams present financing confidently, practices using Alphaeon consistently capture cases that would otherwise remain lost.
Contact Alphaeon Credit at 1-920-306-1794 or email teamcredit@alphaeon.com to learn how flexible financing can help your practice recover revenue from patients who said "not yet"—and turn them into patients who say "yes."

The Mid-year Conversion Stack How AI + Instant Financing Turn Inquiries Into Booked Procedures
What happens when you combine AI-powered patient engagement with instant patient financing?
More inquiries become consultations.
More consultations become booked procedures.
More patient interest turns into growth.
Join us on June 26 as Dr. Shitel Patel, MD, Board-Certified Surgeon, CEO, and Co-Founder of AdVital, shares how leading practices are leveraging AI and financing to improve conversion throughout the patient journey.
In this session, you'll learn:
✔ How AI is transforming speed-to-lead and patient engagement
✔ Why patients hesitate—and how to reduce decision friction
✔ How instant financing helps patients move forward with confidence
✔ Strategies to improve conversion without increasing acquisition costs
✔ What the modern "conversion stack" looks like for growth-focused practices
As patient acquisition costs continue to rise, the practices that win won't necessarily generate more leads—they'll convert more of the leads they already have.
📅 June 26
🕛 12:00 PM CST
Register today https://attendee.gotowebinar.com/register/8330973671364887648.

CareStack and Alphaeon Announce New Integration
New integration streamlines patient financing within CareStack's practice management platform, making it easier for providers to help patients move forward with care.
NEWPORT BEACH, Calif., June 23, 2026 /PRNewswire/ -- CareStack, a leading cloud-based dental practice management platform, and Alphaeon Patient Financing, a premier patient financing solution designed for elective healthcare, today announced the launch of a new integration that helps practices seamlessly incorporate patient financing into their existing workflows.
The integration is designed to address one of the most significant challenges facing healthcare providers today: helping patients confidently move forward with treatment in an environment where patient financial responsibility continues to rise.
"Financial concerns remain one of the biggest barriers between patients and treatment," said Abhi Krishna, Chief Executive Officer of CareStack. "By integrating Alphaeon into CareStack, we're helping practices make accessible financing part of the care journey, enabling more patients to move forward with recommended treatment, while improving case acceptance and practice growth for our customers."
By connecting CareStack's comprehensive practice management capabilities with Alphaeon's financing platform, providers can offer patients flexible payment options directly within their workflow, reducing financial friction, improving operational efficiency, and increasing treatment acceptance.
"Patients are increasingly seeking flexible ways to pay for care, and providers need tools that make those conversations easier," said Thomas Ervesun, Chief Executive Officer, Alphaeon. "By integrating Alphaeon directly within CareStack, we're helping practices remove barriers that often stand between patients and treatment. Together, we're creating a better experience for providers, staff, and the patients they serve."
Addressing a Growing Industry Challenge
As deductibles, out-of-pocket expenses, and elective treatment costs continue to rise, financial concerns have become one of the leading reasons patients delay or decline recommended care.
For practices, this often results in:
Lower case acceptance rates
Delayed treatment starts
Lost production opportunities
Increased pressure on front-office teams
Slower revenue growth
The new CareStack and Alphaeon integration helps practices proactively address these challenges by making financing more accessible, visible, and actionable at the point of care.
Key Benefits of the Integration
The integration enables practices to:
Present financing options within existing workflows
Reduce administrative burden on clinical and front-office teams
Help patients make informed treatment decisions with confidence
Improve treatment conversion and case acceptance rates
Increase revenue opportunities through higher treatment completion
Deliver a more convenient and patient-friendly financial experience
Supporting Practice Growth Through Better Financial Experiences
The integration reflects a growing trend among leading healthcare organizations: recognizing that patient financing is no longer simply a payment solution, but a strategic growth tool.
When patients have access to financing options that fit their needs, providers can help more patients move forward with treatment plans, improve patient satisfaction, and strengthen practice performance.
With Alphaeon's industry-leading provider support, competitive financing offers, and patient-first approach combined with CareStack's modern cloud-based platform, practices now have a powerful solution to help drive both operational efficiency and practice growth.
Availability
The CareStack and Alphaeon integration is now available to eligible CareStack customers.
To learn more about the integration and upcoming educational opportunities, visit myalphaeoncredit.com/carestack.
About CareStack
CareStack is a leading cloud-based dental practice management platform designed to simplify operations, improve patient engagement, and help dental organizations scale efficiently. Its all-in-one platform supports scheduling, clinical workflows, billing, analytics, patient communications, and more for practices of all sizes.
About Alphaeon
Alphaeon is a patient financing solution that helps patients access elective healthcare procedures and treatments through flexible payment options. Trusted by providers nationwide, Alphaeon helps practices improve patient affordability, increase treatment acceptance, and support long-term growth backed by a 24/7 provider-hotline answered in 60 seconds or less. Learn more about our provider solutions at myalphaeoncredit.com.

CareStack Customer Exclusive
Unlock More Growth with the New Alphaeon Integration
Your practice already relies on CareStack to streamline operations, improve efficiency, and deliver a better patient experience.
Now it's time to unlock even more growth.
Join CareStack and Alphaeon on June 23rd for an exclusive customer webinar showcasing the newest CareStack–Alphaeon Patient Financing integration and how practices are using it to remove financial barriers, increase treatment acceptance, and make financing easier than ever for both patients and staff.
Why You Can't Afford to Miss This
Every day, patients leave treatment plans undecided—not because they don't want care, but because they're unsure how they'll pay for it.
The result?
Delayed treatment
Lower case acceptance
Lost production
Missed revenue opportunities
The new CareStack and Alphaeon integration helps solve this challenge by embedding financing directly into your workflow, making it easier for your team to present options, support patient decisions, and help more patients move forward with treatment.
What This Integration Unlocks for Your Practice
✔️ Higher case acceptance and treatment conversion
✔️ Faster, more confident patient decisions
✔️ Improved cash flow and production growth
✔️ Less administrative burden on your team
✔️ A seamless workflow between practice management and financing
✔️ Better patient experiences with flexible payment options
When financing becomes easier to present and easier for patients to access, more treatment plans become completed treatment—and that's where real growth happens.
What You'll Learn
How patient financing directly impacts practice growth, revenue, and cash flow
Where practices lose patients due to financial uncertainty—and how to prevent it
How the new integration simplifies financing conversations inside your existing CareStack workflow
Best practices for increasing case acceptance without creating pressure for patients
What makes Alphaeon different, including competitive offers, higher approval opportunities, and dedicated provider support
Featuring Experts from CareStack & Alphaeon
Hear directly from leaders at both organizations as they demonstrate how practices are connecting operations and financing to create a more seamless—and more profitable—patient journey.
Bonus for Attendees
Join us live and we'll treat you to:
☕ Coffee on us — Every attendee receives a coffee gift card
🍽️ Chance to Win a $300 Summer Team Lunch — One lucky practice will receive a catered lunch for their team
This is more than a product update.
It's an opportunity to learn how to help more patients say yes, support your team with better tools, and unlock additional growth from the patients already walking through your doors.
Register now and discover what's possible with the newest CareStack–Alphaeon integration.
We look forward to seeing you on June 23rd!
The CareStack & Alphaeon Teams

The Summer Slowdown Is Coming: How Patient Financing Can Protect Your Practice Revenue

Every practice owner knows the pattern. As temperatures rise and vacation season kicks in, appointment calendars start showing gaps. Patients postpone elective procedures, delay treatment plans, and prioritize family trips over follow-up visits. The summer slowdown is a predictable challenge—but it doesn't have to mean predictable revenue losses.
What many practices overlook during slower months is that patient hesitation often isn't about timing at all. It's about money. The family vacation competing with that cosmetic procedure? The summer camp tuition that's bumping the LASIK consultation? These aren't necessarily either/or decisions—not when patients have access to flexible payment options that let them manage both.
Here's how strategic patient financing can transform your practice's summer from a revenue valley into surprisingly strong months.
The Psychology Behind Summer Postponement
When patients delay treatment during summer months, they rarely articulate the real reason. They'll mention busy schedules, travel plans, or wanting to "wait until fall." But dig deeper, and a financial calculation is almost always at play.
Summer brings concentrated expenses for many households: vacations, camp fees, back-to-school shopping on the horizon, home improvement projects. These competing demands make large out-of-pocket healthcare expenses feel particularly burdensome—even for patients who could technically afford them.
The key insight? Many of these patients aren't saying "no" to treatment. They're saying "not right now, not all at once." That's a fundamentally different objection, and it's one that patient financing directly addresses.
Reframing the Conversation
Consider how the treatment acceptance conversation typically unfolds:
Without financing: "The total for your treatment plan is $4,500. How would you like to pay?"
The patient mentally calculates that $4,500 against summer expenses, feels the weight of the number, and says they'll "think about it" or "schedule after Labor Day."
With financing presented upfront: "Your treatment plan totals $4,500. Many of our patients find it easier to manage this as monthly payments—often under $150 per month with our financing options. Would you like to see what you'd qualify for? It takes about two minutes and won't affect your credit score."
Now the patient is comparing $150 per month against their budget, not $4,500. That's a fundamentally different mental calculation—and one that often leads to "yes, let's do it now."
Why Summer Is Actually Ideal for Many Procedures
Here's what your front desk team should be communicating: summer can actually be the better time for many elective procedures.
Recovery time: Patients with flexible summer schedules—teachers, students, parents coordinating around school calendars—may have more time to recover than they will during the busy fall.
Advance booking advantage: Scheduling now means securing preferred appointment times before the fall rush when everyone who "waited until after summer" calls at once.
Results timing: Patients who want to look their best for fall events, holiday photos, or year-end celebrations need to start treatment now.
Promotional opportunities: Summer slowdowns create opportunities for practices to offer promotional financing terms that might not be available during peak seasons.
Patient financing transforms summer's perceived disadvantage—competing expenses—into an actual advantage: payments spread over time align beautifully with patients who have more time for recovery.
Proactive Outreach to Pending Treatment Plans
Most practices have a list of patients who received treatment recommendations but haven't scheduled. Summer is the perfect time to revisit these conversations with a financing-forward approach.
Consider outreach messaging like:
"Hi [Patient Name], I'm reaching out from [Practice Name] about the treatment we discussed back in [month]. I wanted to let you know that we now have some flexible payment options that many patients are finding really helpful. If budget was a factor in your decision to wait, I'd love to share what's available—there's no obligation, and checking won't affect your credit score. Would you have a few minutes to talk this week?"
This approach does several things: it acknowledges (without assuming) that cost may have been a factor, it introduces a solution, and it removes the perceived risk of exploring options.
Training Your Team for Summer Success
Your front desk and treatment coordinators are the difference between financing being utilized and financing being forgotten. Summer is an excellent time to invest in training that ensures your team:
Introduces financing early. Patients should hear about payment options before they see final numbers—not as a last resort after sticker shock has set in.
Normalizes the conversation. Language matters. "Would you like to apply for financing?" sounds remedial. "Would you like to see your monthly payment options?" sounds helpful.
Understands the approval process. Team members confident in explaining soft credit checks, approval timelines, and payment structures will present financing more naturally.
Follows up effectively. Patients who check their options but don't proceed immediately should receive thoughtful follow-up—not aggressive sales pressure, but genuine check-ins.
Alphaeon Credit offers training resources and ongoing support specifically designed to help practice teams become comfortable and confident with patient financing conversations. Summer's slower pace makes it the ideal time to invest in this training.
Leveraging Multiple Financing Tiers
Not every patient has the same credit profile, and single-tier financing solutions leave money on the table. Practices partnering with financing providers that offer multiple approval tiers—from prime to near-prime to subprime—capture cases that would otherwise walk out the door.
With multi-tier solutions like those offered through Alphaeon Credit, a single application can match patients with the financing option best suited to their credit profile. More approvals mean more scheduled procedures, more revenue, and more patients receiving the care they need.
During summer months, when every case matters more to your bottom line, these expanded approval rates become particularly valuable.
Marketing Financing Proactively
Don't wait for patients to ask about payment options. Make financing part of your summer marketing:
Website visibility: Ensure payment options are prominently featured, not buried in a FAQ page. Patients researching your practice should immediately see that flexible payments are available.
Social media: Posts highlighting payment plan availability normalize the conversation before patients ever contact you.
Email campaigns: Reach out to your patient base with messaging focused on accessibility: "Great care shouldn't require waiting. Ask about our flexible payment plans."
In-office signage: Counter cards, posters, and waiting room materials should remind patients that options exist.
Consultation integration: Treatment coordinators should present financing as a standard part of every consultation, not a fallback.
Alphaeon Credit provides marketing materials and resources to help practices communicate financing availability effectively across all these channels.
The Math That Matters
Consider the real impact of converting even a few "I'll wait until fall" responses into "Let's move forward now" decisions:
If your average elective procedure generates $3,000 in revenue, converting just four additional patients per month through financing availability represents $12,000 in monthly revenue that would have otherwise been delayed—or lost entirely to a competitor who made payment easier.
Over a three-month summer period, that's $36,000 in revenue protected. And because those patients are now in your active treatment cycle, they're also more likely to return for maintenance, follow-up, and additional services.
Building Year-Round Financial Accessibility
The strategies that protect summer revenue don't stop working when fall arrives. Practices that build patient financing into their standard operations see benefits throughout the year:
Higher case acceptance rates across all seasons
Larger average transaction sizes (patients pursue comprehensive treatment plans when monthly payments are manageable)
Improved patient satisfaction (financial flexibility reduces stress and improves the overall care experience)
Competitive differentiation (patients increasingly expect payment options)
Reduced accounts receivable challenges (financing partners pay the practice while patients pay over time)
Summer may be the catalyst for integrating financing more deeply into your practice, but the benefits compound year after year.
Partner With Alphaeon Credit
For over a decade, Alphaeon Credit has helped healthcare practices turn financial obstacles into treatment acceptance. Our platform is built specifically for elective healthcare—dental, vision, aesthetics, audiology, veterinary, and beyond—with features designed around how these practices actually operate.
With credit lines up to $25,000, multi-tier approval options that expand your approval spectrum, and a dedicated practice support hotline answered by real people (not phone trees), Alphaeon Credit partners with your team to make financing work for your patients and your practice.
Enrollment is free, setup is fast, and training is available to ensure your team is confident from day one.
Don't let summer become a revenue gap. Visit myalphaeoncredit.com/get-started to enroll your practice, or call our practice support team to learn more about how patient financing can transform your seasonal revenue patterns.